Colon and Rectum
Stoma Prolapse and Retraction
Stoma prolapse is the telescoping of the intestine out of the stoma opening, while retraction is the sinking of the stoma below the level of the skin.
Reviewed by Allen Kamrava, MD, MBA, FACS, FASCRS · Last reviewed 2025-10-12
Overview
What are stoma prolapse and retraction?
Stoma prolapse and stoma retraction are two common structural complications that can occur after ostomy surgery. They represent opposite problems with the length of the stoma.
- Stoma Prolapse: This is a condition where the intestine protrudes or telescopes out from the stoma opening, making it much longer than it was originally. It can be a frightening sight, but it is often not a serious medical problem. Prolapse is more common with loop colostomies than with end ileostomies.
- Stoma Retraction: This is the opposite problem, where the stoma pulls back, or sinks, to a level that is flush with or below the skin. This can make it very difficult to maintain a good seal with the ostomy appliance, leading to frequent leakage and skin problems.
Symptoms
What are the symptoms?
Stoma Prolapse:
- A visible lengthening or telescoping of the stoma. The prolapsed portion may be a few centimeters to over a foot long.
- The prolapse may come and go, often being more prominent with coughing, straining, or standing.
- Difficulty with pouching, as the size and shape of the stoma changes.
- The prolapsed stoma may become swollen, irritated, or ulcerated from rubbing against the pouch.
- In rare cases, the prolapse can become trapped (incarcerated) and lose its blood supply, causing severe pain and a change in color to a dark red or purple.
Stoma Retraction:
- The stoma is at or below the level of the skin.
- Frequent leakage of stool underneath the skin barrier.
- Severe peristomal skin irritation, pain, and skin breakdown.
- Difficulty getting an ostomy appliance to stick for more than a short period of time.
Causes & risk factors
What causes stoma prolapse and retraction?
Stoma Prolapse:
- Weak Abdominal Muscles: Weakness in the abdominal wall provides less support for the intestine.
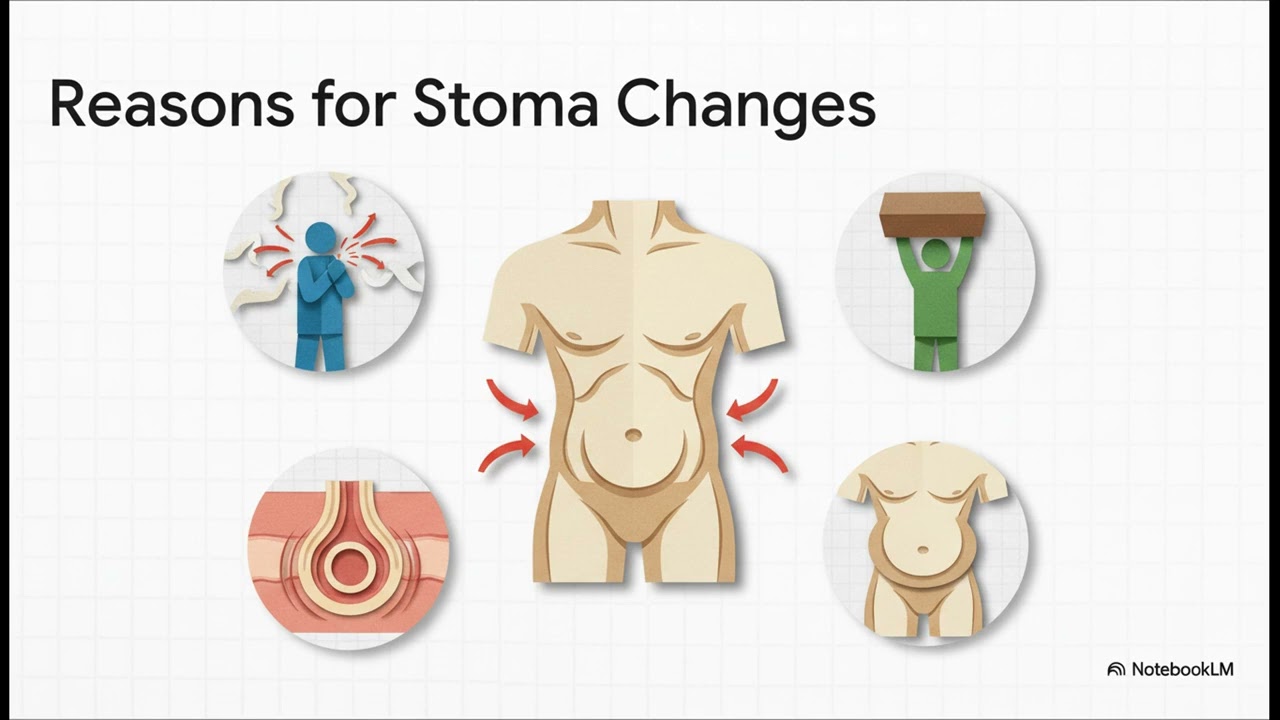
- Increased Intra-abdominal Pressure: Obesity, pregnancy, chronic coughing, and heavy lifting all increase pressure that can push the bowel out.
- Large Opening in the Abdominal Wall: If the opening made for the stoma is too large, it can allow the intestine to slide out.
- Technical Factors: A loop stoma that is not properly secured or an end stoma made from a very mobile segment of bowel may be more prone to prolapse.
Stoma Retraction:
- Tension: If there was not enough length in the intestine to create a tension-free stoma at the time of surgery, it may pull back over time.
- Weight Gain: Gaining a significant amount of weight after surgery can increase the thickness of the abdominal wall, causing the stoma to become retracted.
- Ischemia: Poor blood supply to the stoma immediately after surgery can cause the tissue to die and pull away, leading to retraction and stenosis (narrowing).
- Scarring: Chronic inflammation or skin problems around the stoma can lead to scarring that pulls the stoma inward.
When to see a doctor
When should I see a doctor?
You should contact your surgeon or a stoma nurse if you notice a significant change in the length or appearance of your stoma.
For a prolapse, you should seek care if:
- It is causing discomfort or problems with pouching.
- The stoma appears swollen, irritated, or has developed sores.
- You cannot reduce the prolapse yourself.
For a retracted stoma, you should seek care if you are having persistent leakage and skin problems that cannot be managed with pouching adjustments.
Urgent — get care now
When is it an emergency?
A prolapsed stoma becomes an emergency if its blood supply is compromised. Seek immediate medical attention if a prolapsed stoma:
- Becomes suddenly very painful.
- Changes color to a dark red, purple, or black.
- Stops functioning (no stool or gas output).
A retracted stoma is not typically an emergency.
Diagnosis & tests
How are these conditions diagnosed?
The diagnosis of both stoma prolapse and retraction is made by physical examination. The length, appearance, and function of the stoma are assessed. Your healthcare provider will also examine the surrounding skin and the fit of your ostomy appliance.
Treatment
How are stoma prolapse and retraction treated?
Treatment depends on the severity of the symptoms.
Stoma Prolapse:
- Manual Reduction: Often, a prolapse can be gently pushed back in. Lying down can help. Applying cool compresses or a small amount of sugar to the prolapsed stoma can help reduce swelling and make reduction easier.
- Support: Wearing an ostomy support belt can help to keep the prolapse reduced.
- Pouching Adjustments: You may need a larger pouch to accommodate the prolapsed stoma.
- Surgery: Surgical repair is reserved for cases that are causing significant symptoms, cannot be reduced, or show signs of compromised blood supply. Surgery may involve repairing the stoma at its current site or moving it to a new location.
Stoma Retraction:
- Pouching Adjustments: This is the mainstay of treatment. A stoma nurse can help you find a system that works for your retracted stoma. This almost always involves using a convex skin barrier. Convexity helps to push the skin down around the stoma, allowing the stoma to protrude slightly and creating a better seal. An ostomy belt is often used with a convex barrier to apply gentle pressure.
- Surgery: If leakage and skin problems cannot be controlled with specialized pouching systems, surgical revision of the stoma may be necessary. This involves re-mobilizing the intestine and creating a new stoma that protrudes properly.
Frequently asked questions
Is a prolapsed stoma dangerous?
Most of the time, a stoma prolapse is not dangerous, just inconvenient and sometimes uncomfortable. The main concern is that the blood supply to the prolapsed intestine could be cut off, which is a rare but serious emergency.
Can I just live with a retracted stoma?
If you can achieve a good, leak-proof seal with a convex pouching system and your skin is healthy, then there is no need for surgery. The goal is to be comfortable and leak-free. If this cannot be achieved, then surgical revision should be considered.
Will surgery fix the problem for good?
Surgery for both stoma prolapse and retraction has a risk of recurrence. The underlying factors that caused the problem, such as weak abdominal muscles or obesity, may still be present. This is why surgery is usually only considered when non-surgical options have failed.
References
- McGee MF, Cataldo PA. Intestinal Stomas. In: Steele SR, Hull TL, Hyman N, Maykel JA, Read TE, Whitlow CB, eds. The ASCRS Textbook of Colon and Rectal Surgery. 4th ed. Springer; 2022:907-945.
- Cleveland Clinic. Prolapsed Stoma. Accessed September 28, 2026. https://my.clevelandclinic.org/health/diseases/prolapsed-stoma
- Ostomy Canada Society. Stoma Prolapse, Stenosis, and Retraction. Accessed September 28, 2026. https://www.ostomycanada.ca/blog/2025/stoma-prolapse-stenosis-retraction/